How to Build a Coding Compliance Program (Before the Auditor Does It for You)
November 16, 2026 · 16 min read
A coding compliance program is the documented system a healthcare practice uses to prevent, detect, and correct coding errors before they become payer audit findings or overpayment demands. It applies the OIG's compliance framework directly to your coding and billing operations. Without one, you are not just billing without oversight; you are accumulating liability that compounds every claim cycle.
Payers run audits. Medicare Administrative Contractors pull records. The OIG publishes its Work Plan every year, and E/M coding, behavioral health CPT codes, and modifier usage appear on it routinely. If your coding operation consists of "we hired a good coder," you are not running a compliance program. You are running a hope-based billing strategy.
Here is what a real one looks like.
What Your Coding Compliance Program Needs to Include
The OIG's General Compliance Program Guidance, updated November 6, 2023, organizes every effective compliance program around seven elements. For coding-specific programs, four of those elements do the heaviest lifting. The other three govern what happens when audits find something.
| Program Component | What It Covers | Minimum Frequency |
|---|---|---|
| Written standards and policies | Code selection criteria, documentation requirements, modifier rules, prohibited practices | Annual review and update |
| Training and education | Coder accuracy, provider documentation coaching, annual code updates | At least annually; quarterly for high-risk codes |
| Communication channel | Mechanism for staff to raise concerns without retaliation | Ongoing |
| Auditing and monitoring | Internal chart review, prospective and retrospective | Quarterly minimum |
| Compliance oversight | Who owns the program and reports on it to leadership | Ongoing |
| Enforcement | Consequences for violations, applied consistently | As needed |
| Corrective action | Retraining, refunds, process changes when errors are found | Within 60 days of finding |
This framework is voluntary. Courts and regulators treat it as the standard, though. If your practice is under investigation and has no documented compliance program, that absence becomes part of the record against you.
The OIG Updated Its Framework in 2023. Here Is What Actually Shifted.
Before November 2023, the OIG issued sector-specific compliance guidance for physician practices, hospitals, and third-party billers separately. The 2023 General Compliance Program Guidance consolidated all of that into one document that applies across the entire industry.
The seven elements themselves are largely the same as the late-1990s framework. What changed is the emphasis.
Board-level accountability. Leadership is now expected to understand and actively oversee the compliance program, not just sign off on a policy binder once a year.
Risk-based audit scheduling. The 2023 GCPG is explicit: audits should be driven by an annual compliance risk assessment, not by routine habit. That means identifying which CPT code families, service lines, or providers carry the most audit exposure before you decide what to review.
Stronger corrective action requirements. Finding an error and doing nothing is itself a compliance failure under the updated framework. A program without documented corrective action cycles does not satisfy OIG expectations.
For coding programs specifically, written policies on machine-assisted coding tools and copy-paste risk in EHRs are an increasingly important part of program completeness. If your practice uses AI-assisted coding tools or coders are pulling forward documentation from previous visits, your written standards need to address those practices directly.
How to Run the Coding Compliance Audit
This is where most programs break down. The policies exist. Someone did a training. The audit never actually happens, or it happens and nobody tracks results against a threshold that means anything.
A functioning coding compliance audit works in three stages.

Start with a baseline
If you are establishing a new program, or if the program has never been formally documented, begin with a baseline audit. Pull a cross-section of claims covering your highest-volume CPT codes and payors. Sample 10–25 records per provider across at least one full quarter. The goal is to understand your current error rate before you do anything else.
The OIG's older physician practice guidance recommended 5–10 records per physician at minimum. Most compliance consultants today push that to 15–25 for a defensible baseline, especially in multispecialty groups where code distribution varies considerably by provider.
Move to quarterly cycle audits
After baseline, run quarterly audits. Rotate through providers and service lines based on your risk assessment: whichever CPT codes have the highest denial rate, the most modifier complexity, or the greatest documentation variability.
For small practices, 10–25 claims per provider per quarter is a defensible sample. For larger groups, use stratified sampling across service lines rather than a flat random pull.
Know what your error rate actually means
Your compliance program needs an explicit written policy on what error rate triggers escalation. Here is the standard framework most programs use:
| Error Rate | Category | What It Requires |
|---|---|---|
| Below 5% | High-performing | Document and monitor; no escalation needed |
| 5–10% | Elevated concern | Targeted retraining; re-audit within 60–90 days |
| 10–15% | Problematic | Mandatory education, formal corrective action plan |
| Above 15% | High risk | Full expanded audit, refund assessment, possible self-disclosure |
The OIG treats a 5% net financial error rate as the trigger for full sample review in Corporate Integrity Agreements. For internal programs, most treat anything above 5% as requiring immediate action rather than monitoring.
Track both a record error rate (claims with at least one error divided by total audited) and a dollar error rate (net dollar discrepancy divided by total dollars audited). The dollar rate tells you whether you have a liability problem or a training gap.
When Audits Find Something
Finding errors in a coding audit is normal. Finding errors and doing nothing is a compliance violation.
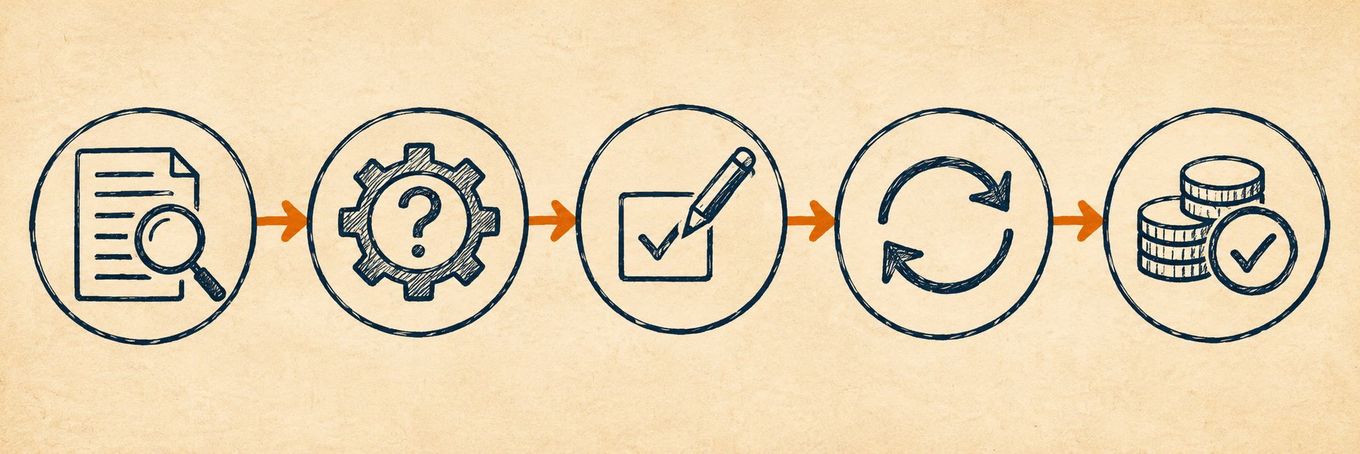
A defensible corrective action cycle:
- Document the finding: error type, volume, affected providers, dollar impact.
- Determine the cause: training gap, documentation failure, coder misunderstanding of payer policy, or a system configuration problem.
- Implement the fix: retraining, documentation templates, claim edits, or workflow changes.
- Re-audit within 60–90 days. The re-audit is what proves the fix worked.
- Assess refund obligation. If errors resulted in overpayments, the practice has 60 days from identification to refund or formally report the overpayment under the ACA's self-disclosure rules. That clock runs from when you knew about the error.
The 60-day window is where practices get into serious trouble. Missing it converts an overpayment into potential False Claims Act exposure. The compliance program has to have a written trigger that initiates overpayment assessment as soon as a systematic error is confirmed.
Accurate coding and clean claims are the upstream side of this. A strong denial management process catches problems as they hit the payer. For how to manage the downstream side when claims come back, our guide on denial management covers what an effective appeals and tracking process looks like.
What Your Compliance Program Needs to Document
The compliance program lives on paper. If your practice is ever audited or investigated, the documentation you have produced over time is what proves the program was real and functioning, not just a folder someone printed and filed once. These are the records a defensible program maintains.
| Document | What It Proves | Retention |
|---|---|---|
| Written policy and procedure manual | The program existed and defined standards before any finding | Ongoing; update at minimum annually |
| Annual compliance risk assessment | Audit calendar was risk-driven, not random | At least 3 years |
| Training attendance records | Coders and providers completed required education | At least 6 years |
| Audit work papers | Methodology, sample selection, records reviewed, findings, error rate calculations | At least 6 years |
| Error rate tracking by provider and code family | Program monitored trends, not just one-off audits | At least 3 years |
| Corrective action plans | Errors were addressed with documented follow-through | At least 6 years |
| Overpayment refund records | Repayments were made within the 60-day window | At least 6 years |
The six-year retention figure for audit records aligns with the False Claims Act statute of limitations. If a claim from two years ago is challenged, you need records showing your compliance cycle was running during that period, not just records from the most recent audit cycle.
Training sign-off records are the most commonly missing documentation in practices that believe they have a functioning program. A policy binder without evidence that staff actually received and acknowledged that training does not satisfy OIG expectations for the training and education element.
One practical note on audit work papers: the records should document your methodology (how you selected the sample, what codes you focused on, why) not just your findings. A sample list of records reviewed with no explanation of how they were selected is not a defensible audit trail.
Behavioral Health Adds Its Own Layer
If you are running a behavioral health, mental health, or psychiatry practice, your coding compliance program needs to address a few specific risk areas that general guidance tends to gloss over.

Time-based psychotherapy codes. CPT codes 90837, 90834, and 90832 are selected based on session time, with add-on codes 90833, 90836, and 90838 paired with E/M codes when both a medical and psychotherapy service occur in the same visit. Your documentation needs to capture start and stop times. Coders need to apply the OIG's midpoint rounding rules correctly. Consistently billing 90837 (53 minutes or more) without documentation to support that time range is exactly the kind of statistical pattern that flags on a payer audit.
E/M and add-on code pairings. When a prescriber conducts an evaluation and management visit that also includes a psychotherapy component, the correct claim pairs an E/M code with the appropriate add-on. Billing a standalone psychotherapy code when an E/M was performed generates denials from most major commercial payers and flags on Medicare audit protocols.
Telehealth modifier compliance. Modifier 95 usage, originating site rules, and ongoing payer-specific telehealth policies all require documented policies and periodic audit attention. This area changes fast enough that written standards need at least an annual review cycle.
Behavioral health billing has payer-specific requirements that layer on top of the general compliance framework. The compliance program has to reflect those specifics, not just the OIG's general guidance.
For a broader look at how behavioral health coding works across CPT code families, the mental health billing guide covers the most common coding and documentation issues in detail.
How to Use the OIG Work Plan to Build Your Audit Calendar
The OIG publishes its Work Plan throughout the year, listing the specific billing patterns, CPT code families, and service lines it is actively investigating across Medicare and Medicaid. Coding compliance programs that align their audit rotation to Work Plan priorities are more defensible than ones that audit by habit or convenience. If a code family is on the Work Plan, the OIG already suspects a systemic problem there, and Medicare Administrative Contractors are likely pulling records in that area.
Perennial Work Plan focus areas that appear in most specialties:
| Work Plan Category | Why It Gets Flagged | What Your Audit Should Check |
|---|---|---|
| E/M level selection | High frequency of level 4 and 5 codes | Medical necessity documentation, MDM vs. time-based selection accuracy |
| Psychotherapy session time codes | Inconsistent documentation of session duration | Start/stop time notation, correct code selection by documented minutes |
| Modifier 25 | Unbundling concerns on same-day E/M and procedure claims | Medical necessity documentation for the separate E/M service |
| Split/shared billing | Attending vs. resident documentation confusion | Teaching physician attestation requirements |
| Telehealth billing | Rapid expansion created widespread inconsistencies | Modifier 95 usage, originating site documentation, payer-specific rules |
The process for translating this into an audit calendar is straightforward:
- Review the OIG Work Plan throughout the year at oig.hhs.gov; it is updated monthly, with new audit priorities added in any update cycle.
- Flag any code families or service lines that overlap with your practice's billing volume.
- Front-load those into Q1 of your internal audit rotation.
- Document in your audit work papers that the selection was risk-informed.
That last step matters more than it sounds. If a payer questions your compliance program, being able to show that your internal audit targeted the same CPT families the OIG was investigating that year is materially different from auditing whatever was convenient. A risk-informed audit calendar does not just make your program more efficient; it makes it defensible.
Payer-specific denial patterns are a secondary source for audit prioritization. Code families generating repeated denials are pointing at the same documentation and selection problems a compliance audit would catch. The denial management guide covers how to build that tracking discipline into your revenue cycle operations.
The Coding Violations That Show Up Most Often in Audits
Internal audits find the same patterns repeatedly across practices of different sizes and specialties. Knowing what to look for before you audit is what separates a productive review from one that produces a stack of records and no actionable findings.
| Violation Type | What It Looks Like | How the Audit Catches It |
|---|---|---|
| Upcoding | Consistently billing level 4 or 5 E/M codes regardless of documented complexity | Compare billed level to documented MDM or time; flag outliers above specialty benchmarks |
| Undercoding | Routinely billing level 2 or 3 when documentation supports level 4 or 5 | Same MDM/time comparison, in both directions; undercoding is a revenue leak and sometimes a payer-contract compliance issue |
| Unbundling | Billing separate codes for components that should be billed as a single bundled code | Cross-reference claims against NCCI edit pairs; unbundled codes create edit failures or inappropriate reimbursement |
| Modifier 25 abuse | Appending modifier 25 to same-day E/M services without documentation supporting medical necessity for the separate evaluation | Pull claims with modifier 25 and review documentation; modifier must be supported by a separately identifiable E/M, not just the procedure note |
| Medical necessity failures | ICD-10 diagnosis codes that don't support the billed CPT service, or documentation that describes a service without connecting it to a clinical reason | Confirm that the diagnosis code in the record supports the CPT code billed, and that documentation addresses why the service was necessary |
| Duplicate billing | The same service billed more than once for the same date and patient, often from system or workflow errors | Automated claims data comparison; common after billing system migrations or when multiple coders work the same account |
| Cloning and copy-forward | EHR documentation that looks identical across multiple visits, with no individualization of exam findings or clinical reasoning | Pull records across consecutive visits for the same patient and compare; identical notes are a red flag OIG auditors and Medicare Administrative Contractors consistently flag |
A few of these warrant extra attention.
Undercoding is underweighted in most compliance programs because the error runs in the practice's favor, so it feels less urgent. It is not. Systematic undercoding depresses revenue, and in some payer contracts it may create compliance problems if pattern analysis suggests the practice is cherry-picking which codes to pursue. The fix is the same as for upcoding: audit code selection against documentation for accuracy in both directions.
Cloning sits at the intersection of EHR workflow habits and legal exposure. The OIG has consistently identified copy-paste and copy-forward documentation as a compliance risk area in EHRs, with guidance and audit findings going back more than a decade reinforcing that cloned notes do not constitute defensible documentation. When every visit note for a patient looks identical across six months of records, that documentation is not a defensible basis for the codes attached to it. Auditors, MACs, and payers all flag it. Train coders to identify cloned documentation and to escalate it before it reaches a claim.
Modifier 25 is a perennial Work Plan item for a reason. The modifier exists so practices can receive separate reimbursement for a genuinely separate evaluation on the day of a procedure. The compliance problem arises when modifier 25 is applied reflexively to any same-day E/M, rather than selectively where documentation actually supports it. An audit of modifier 25 usage should include pulling the clinical documentation, not just reviewing the claim.
Why Trust This Article
Clarity Health RCM traces its roots to Quality Medical Billing, founded in 1988. Under President and CEO Estelle Sandoval, our team brings more than 40 years of combined revenue cycle experience across behavioral health practices, inpatient and outpatient physician groups, specialty practices, and hospital-based billing operations.
We know what a compliant coding audit looks like in practice, not just on paper. We also know what a practice looks like when it has let the audit cycle slide for two or three billing cycles. The recovery from the second scenario is significantly more expensive than building the program right the first time.
The regulatory framing in this article draws directly from the OIG's November 2023 General Compliance Program Guidance, available at https://oig.hhs.gov/compliance/compliance-guidance/. Error rate thresholds cited reflect published OIG audit standards and industry audit benchmarks. Nothing in this article constitutes legal, billing, or coding advice for your specific claims or situation.
How Clarity's Coding Audits Fit Into This
If your practice doesn't have the internal bandwidth to run quarterly audit cycles consistently, or if you need external validation to make your program defensible, our coding and auditing service handles the audit layer.
We review claims across your highest-risk CPT code categories, calculate your error and accuracy rates, deliver a written findings report, and work with your team to build a corrective action plan when the audit uncovers patterns that need addressing.
That is not a compliance program by itself. The program lives in your policies, your training, and your internal governance. What we provide is the audit layer that makes it defensible and the subject-matter expertise that catches what internal reviews tend to miss.
Review our coding and auditing services or read how our medical coding services fit into a complete revenue cycle operation.
Frequently Asked Questions
What is a coding compliance program in healthcare?
A coding compliance program is a documented internal system designed to ensure that medical codes submitted on claims are accurate, complete, and consistent with clinical documentation. It incorporates written policies, coder training, regular internal audits, and a corrective action process when errors are found. The OIG's General Compliance Program Guidance, updated November 6, 2023, provides the seven-element framework most compliance programs are built on.
Is a coding compliance program legally required for physician practices?
For most physician practices, a formal coding compliance program is not legally mandated. However, the OIG strongly recommends it, and the absence of a documented program is treated as an aggravating factor during investigations, audits, and False Claims Act cases. Practices under Corporate Integrity Agreements are required to maintain a compliant audit program. Medicare and Medicaid enrollment conditions increasingly expect one.
How often should a coding compliance audit be conducted?
The OIG's 2023 guidance recommends audit schedules driven by your annual compliance risk assessment, with most programs running quarterly internal audits and at least one comprehensive annual review. High-risk service lines or providers with elevated error rates may require more frequent monitoring. A baseline audit is typically run when establishing a new program or after a significant operational change.
What sample size should I use for a coding compliance audit?
For small practices, the OIG's older physician practice guidance suggests 5–10 records per physician at minimum. Most current compliance programs target 10–25 claims per provider per audit cycle for statistical defensibility. Larger groups typically use stratified sampling across service lines. If your probe sample reveals a financial error rate at or above 5%, expand the sample and document the expansion in your audit work papers.
What happens when a coding audit finds errors?
Errors trigger a documented corrective action cycle: identify the error type and volume, determine the root cause, implement a fix, re-audit within 60–90 days, and assess whether any overpayment occurred. If Medicare or Medicaid overpayments are identified, the practice has 60 days from the date of identification to refund or formally report the overpayment under the ACA's self-disclosure rules.
What coding risks are specific to behavioral health practices?
Behavioral health practices face elevated audit risk around time-based psychotherapy code selection (CPT 90837, 90834, 90832), E/M and psychotherapy add-on code pairings (90833, 90836, 90838), telehealth modifier compliance, and documentation of medical necessity for treatment plan-based services. These code families require session time documentation and are frequently flagged on Medicare and commercial payer audits.
What is the difference between a coding audit and a coding compliance program?
A coding audit is a point-in-time review of claims for accuracy. A coding compliance program is the ongoing system that includes audits, written policies, training, oversight, and corrective action. An audit without the supporting program elements does not constitute a compliance program, and it will not satisfy OIG expectations or protect a practice in an investigation.


